PY-60 Intraocular Lens Capsular Bag Positioning Dynamics and Decentration Stability
Copy code to add this image to your page
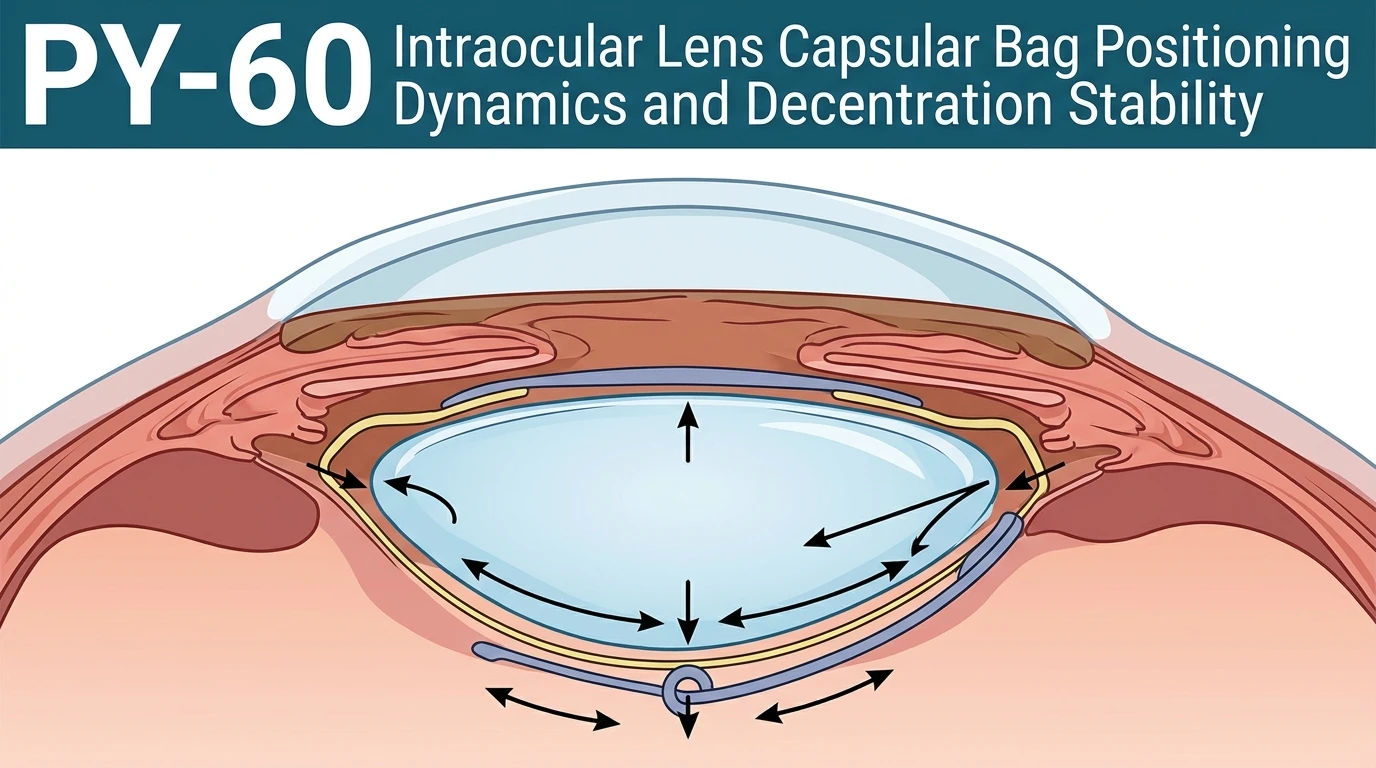
Accurate intraocular lens alignment within the capsular bag represents a critical determinant of optical quality following modern phacoemulsification surgery. Biomechanical interactions between the capsular envelope and the structural haptics of the implanted optic govern long-term spatial stability. Following crystalline lens extraction, continuous myofibroblastic transdifferentiation of residual lens epithelial cells initiates progressive capsular bag shrinkage. This contractile process generates asymmetric radial forces capable of displacing the optical center away from the visual axis or inducing planar tilt. In this context, evaluating specific haptic architectures—such as four-point contact plate-haptic designs versus conventional three-piece C-loop configurations like the PY-60 AD—provides vital empirical data regarding mechanical resistance against post-surgical capsular deformation.
To rigorously assess short-term postoperative spatial alignment, clinical investigators utilized swept-source optical coherence tomography coupled with a customized deep convolutional neural network segmentation pipeline. This advanced imaging approach enabled high-precision three-dimensional biometry of the anterior segment, accurately isolating the anatomical boundaries of both the capsular envelope and the intraocular lens optic. The study evaluated two distinct design paradigms: the single-piece plate-haptic ATTORBI 709 M and the three-piece C-loop PY-60 AD. Quantitative measurements focused on two primary endpoints at early postoperative intervals: absolute planar decentration relative to the pupillary axis and three-dimensional angular tilt relative to the reference corneal plane.
Quantitative analysis revealed substantial performance disparities in lateral spatial stability between the two structural designs. The plate-haptic cohort exhibited a mean decentration of 0.16 ± 0.08 mm. Conversely, the three-piece C-loop PY-60 group displayed a significantly higher mean decentration of 0.42 ± 0.28 mm (p < 0.001). This marked difference highlights the biomechanical advantages of equatorial plate contact. Four planar contact zones distribute localized capsular contractile forces across a broad surface area, preventing translational sliding of the optic within the capsular equator. In contrast, the dual-point contact inherent to C-loop haptic geometry yields higher susceptibility to localized capsular bending forces, permitting lateral translation when asymmetrical shrinkage occurs.
In contrast to planar decentration, postoperative angular tilt demonstrated remarkable structural consistency between design groups. The mean tilt measured 4.60 ± 1.27° for the plate-haptic design and 4.63 ± 1.93° for the C-loop PY-60 optic, presenting no statistically significant variance (p = 0.948). Spatial vector mapping revealed that both pre-existing crystalline lenses and post-surgical optics exhibited a distinct inferotemporal tilt orientation. Linear correlation modeling established a statistically significant relationship between preoperative crystalline lens tilt and postoperative intraocular lens tilt (p < 0.003). These empirical findings demonstrate that postoperative angular tilt is primarily dictated by intrinsic anatomical landmarks—including the natural inclination of the scleral spur and ciliary body plane—rather than physical haptic architecture.
Under the clinical imaging conditions evaluated, plate-haptic designs demonstrated clear superiority in mitigating lateral planar decentration compared to three-piece C-loop optics. Automated neural network segmentation confirmed that while haptic geometry effectively stabilizes the lens against translational forces, it exerts minimal influence over physiological angular tilt driven by native capsular topography. Consequently, surgical planning and lens selection must account for both haptic surface contact dynamics and patient-specific ocular anatomy to optimize postoperative visual outcomes and minimize higher-order optical aberrations.
Biomechanical Dynamics of Haptic Design in Capsular Fixation
Copy code to add this image to your page
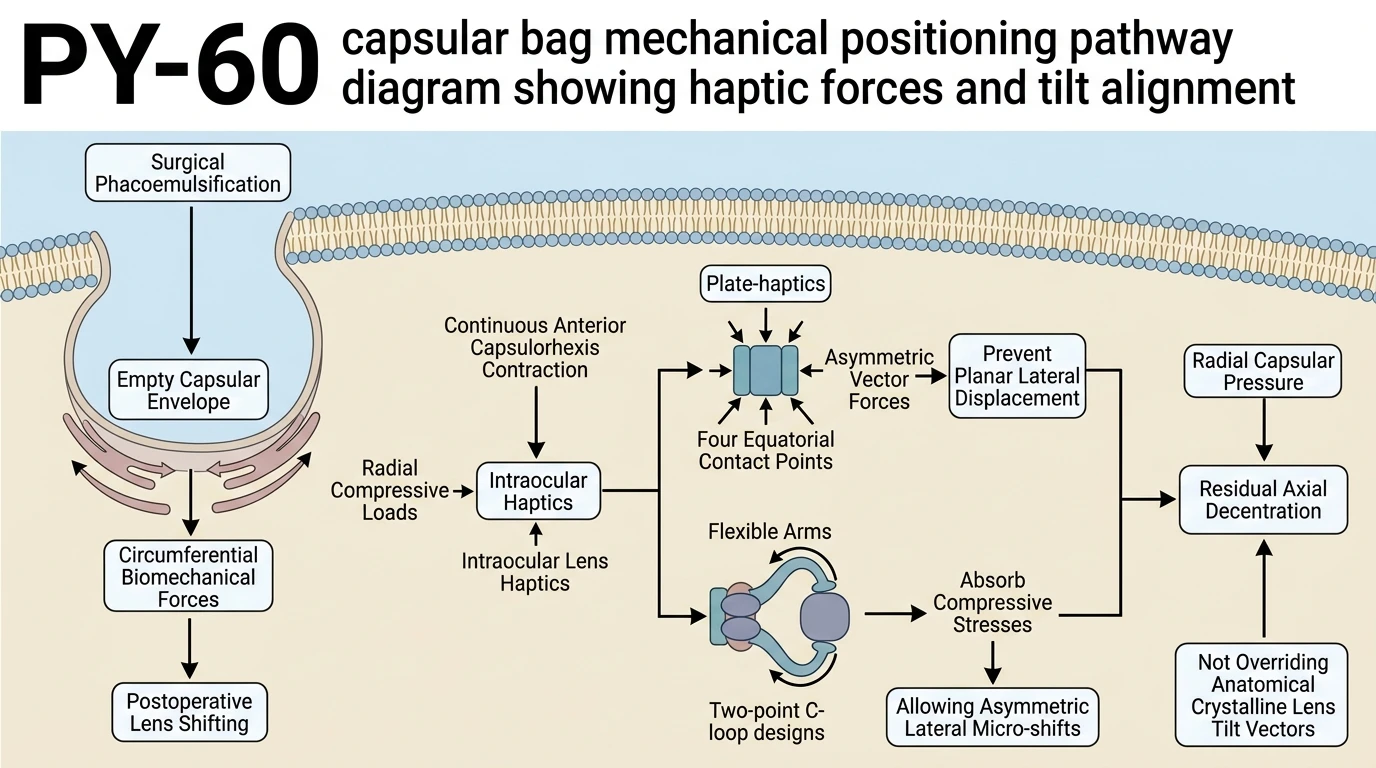
Haptic geometry determines intraocular lens decentration resistance within the capsular bag post-phacoemulsification. Four-point contact plate-haptic designs distribute continuous circumferential capsular contraction stresses across broad equatorial areas, resulting in minimal lateral decentration (0.16 ± 0.08 mm). Three-piece C-loop haptics absorb asymmetric radial contraction via flexible dual contact points, predisposing optics to lateral shifting (0.42 ± 0.28 mm). Angular tilt (4.60–4.63°) is independent of haptic geometry, aligning directly with preoperative crystalline lens inferotemporal anatomical orientation.
Equatorial Four-Point Plate Haptics Mitigate Asymmetric Lateral Decentration
Swept-source optical coherence tomography revealed clear structural differences between haptic configurations. The plate-haptic design maintained superior planar position within the capsular bag. Mean decentration reached 0.16 ± 0.08 mm for plate designs compared to 0.42 ± 0.28 mm for the PY-60 three-piece C-loop variant (p < 0.001). Mechanical contact geometry explains this disparity. Four-point equatorial contact plates convert contractile circumferential forces into uniform axial vector loads. In contrast, two-point flexible haptics yield under localized capsular bag contraction. Asymmetric haptic compression induces lateral planar shifts across the pupillary axis. These empirical observations confirm that broad contact footprints reduce postoperative decentration under physiological capsular shrinkage conditions.
Preoperative Crystalline Lens Tilt Dictates Postoperative Intraocular Lens Orientation
Postoperative tilt metrics remained nearly identical across both structural cohorts. Plate-haptic lenses exhibited an average tilt of 4.60 ± 1.27°, whereas the PY-60 C-loop optic demonstrated 4.63 ± 1.93° (p = 0.948). Anatomical orientation vectors governed these spatial outcomes rather than physical haptic architecture. Both preoperative crystalline lenses and implanted optics exhibited a strong inferotemporal directional bias. Quantitative regression analysis established a significant correlation between native crystalline lens tilt and postoperative lens tilt (p < 0.003). Preexisting anatomical asymmetry dictates angular lens alignment within the eye. Physical haptic modifications fail to alter this primary anatomical orientation. Automated neural network segmentation verified that equatorial scleral geometry dictates overall tilt magnitude across diverse surgical eyes.