Necrostatin 2 racemate attenuates myocardial ischemia-reperfusion injury through RIP1 kinase inhibition
Copy code to add this image to your page
Receptor-interacting serine/threonine-protein kinase 1 (RIP1) operates at the crossroads of cellular stress, inflammatory signaling, and programmed necrosis. During acute myocardial ischemia-reperfusion (I/R) injury, the restoration of cardiac blood flow induces intense oxidative stress that triggers necroptotic cell death. Unlike apoptosis, which proceeds via orderly caspase activation and apoptotic body formation, necroptosis culminates in plasma membrane rupture, releasing damage-associated molecular patterns (DAMPs) into the extracellular space. Small-molecule intervention targeting RIP1 kinase activity offers a focused pharmacological strategy to arrest this necrotic cascade at its inception. Necrostatin 2 racemate (Nec-1s), an optimized derivative of necrostatin-1 with superior metabolic stability and high selectivity for RIP1, serves as a primary tool compound to dissect necroptotic signaling pathways in preclinical cardiovascular models.
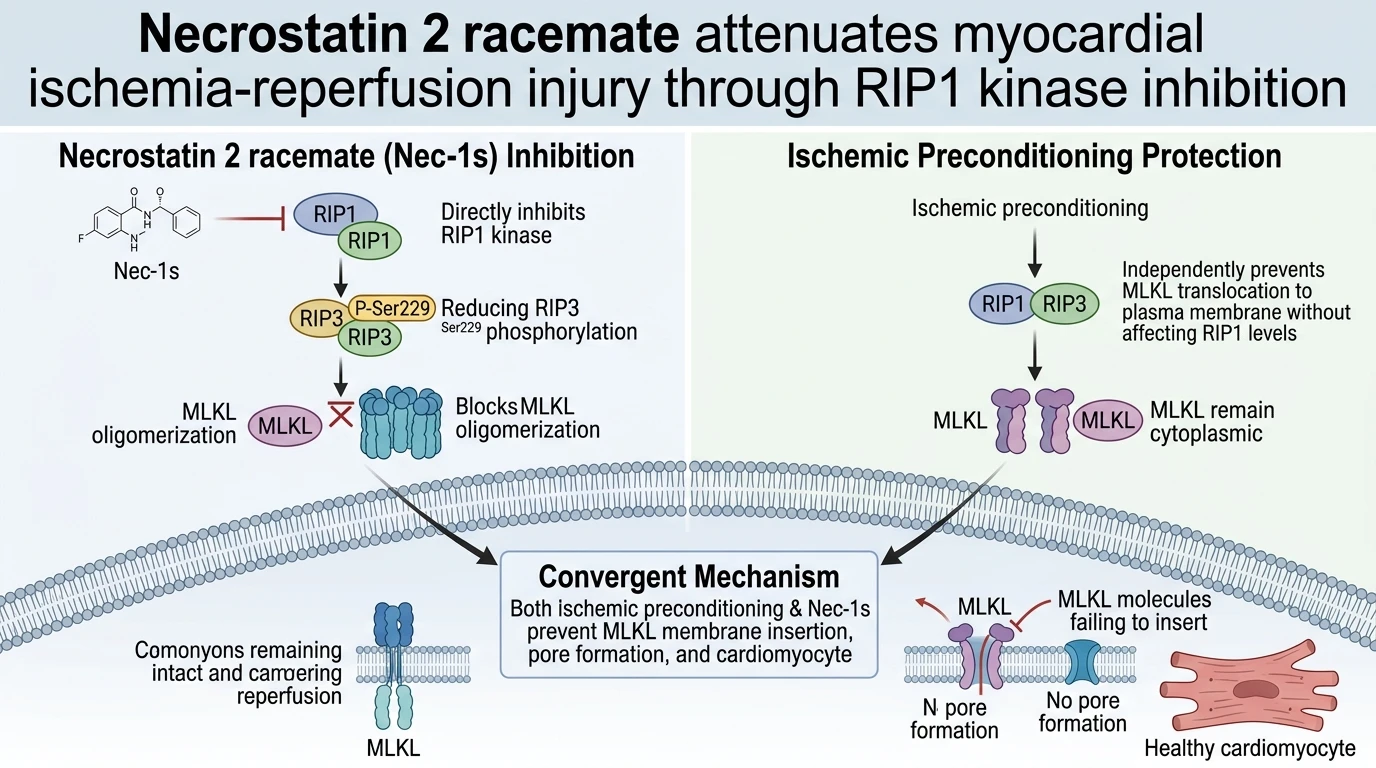
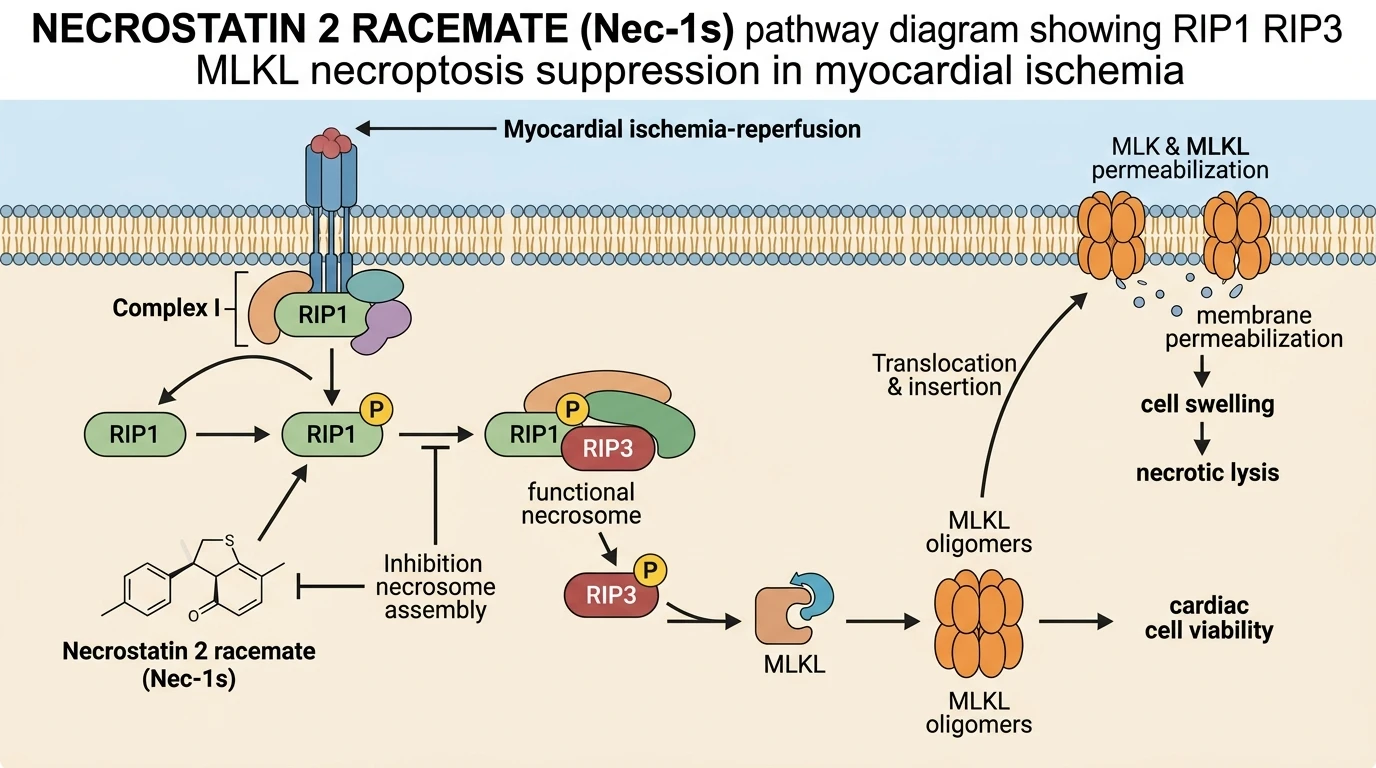
In myocardial tissue subjected to I/R injury, RIP1 autophosphorylation initiates assembly of the necrosome complex through homotypic interaction motifs shared with RIP3. Upon recruitment, RIP3 undergoes autophosphorylation at specific residue sites, notably Ser229, which recruits and phosphorylates the downstream executioner protein mixed lineage kinase domain-like (MLKL). Phosphorylated MLKL undergoes structural rearrangement, shifting from a monomeric soluble state to higher-order oligomers. These MLKL oligomers translocate to the plasma membrane, inserting into phosphatidylinositol-rich lipid domains. Membrane integration disrupts ionic homeostasis, resulting in cell swelling, membrane rupture, and extensive myocardial tissue loss. Necrostatin 2 racemate (Nec-1s) directly blocks the ATP-binding pocket of RIP1, stabilizing the kinase domain in an inactive conformation. By preventing RIP1 trans-phosphorylation, kinase inhibitor pathways in ischemic injury can be precisely modulated to disrupt the canonical necroptotic signaling cascade without blunting non-necroptotic signaling networks.
Comparative investigations evaluating endogenous cardioprotective signaling—specifically ischemic preconditioning (IPC)—against pharmacological intervention with Necrostatin 2 racemate demonstrate equivalent efficacy in limiting myocardial damage. In isolated rodent hearts subjected to index ischemia followed by reperfusion, brief cycles of non-lethal ischemia (IPC) and direct administration of Nec-1s both produced marked reductions in myocardial infarct size. Left ventricular contractile function recovered to comparable levels under both treatments. Notably, concurrent administration of Nec-1s during IPC protocol yielded no additive reduction in infarct size or enhancement of hemodynamic recovery. This lack of additive effect indicates that endogenous preconditioning mechanisms and direct RIP1 inhibition converge on identical downstream necrotic execution nodes.
Biochemical analysis of myocardial tissue lysate reveals that both IPC and Nec-1s suppress MLKL oligomerization and prevent its physical accumulation within plasma membrane microdomains. Despite this shared biological endpoint, the upstream biochemical signatures diverge. Nec-1s specifically reduces pSer229-RIP3 phosphorylation levels, directly confirming target engagement at the RIP1-RIP3 node. In contrast, IPC leaves baseline RIP1 and RIP3 protein levels and phosphorylation states unchanged, operating through distinct endogenous preconditioning cascades that ultimately converge to block MLKL membrane translocation. Furthermore, neither treatment alters markers of lipid peroxidation or apoptotic caspase activation, confirming that the cardioprotection conferred by Nec-1s and IPC stems directly from the selective suppression of necroptotic membrane permeabilization rather than antioxidant or anti-apoptotic pathways.
Quantitative Western blotting and membrane fraction assays demonstrate that under normoxic conditions, MLKL remains localized to the cytosolic fraction as an inactive monomer. Following 30 minutes of global ischemia and two hours of reperfusion, cytosolic MLKL decreases while hydrophobic membrane fractions display dense higher-order MLKL oligomeric bands. Treatment with Necrostatin 2 racemate markedly reduces MLKL signal intensity in the membrane fraction, retaining MLKL in the soluble cytosol. Hemodynamic measurements using intraventricular balloon transducers demonstrate that post-ischemic left ventricular developed pressure (LVDP) and positive first derivative of pressure over time (dP/dt max) improve significantly in Nec-1s treated hearts compared to untreated controls. In cardiac tissue sections stained with triphenyltetrazolium chloride (TTC), infarct area relative to total area at risk decreased from over 50 percent in vehicle controls to below 25 percent in treated groups. These findings establish that direct pharmacological inactivation of RIP1 kinase by Necrostatin 2 racemate provides robust functional preservation of cardiac tissue following severe ischemic insult.
Cardioprotective Efficacy and Necroptotic Signaling Dynamics
Copy code to add this image to your page
Necrostatin 2 racemate (Nec-1s) selectively inhibits RIP1 kinase activity, preventing RIP1 autophosphorylation and subsequent necrosome assembly. This inhibition halts downstream pSer229-RIP3 phosphorylation, blocking MLKL conformational transition and oligomerization. Inhibited MLKL fails to translocate and integrate into the plasma membrane, preserving cell membrane integrity and blunting necroptotic cell lysis during myocardial ischemia-reperfusion. Ischemic preconditioning converges on this same execution node by preventing MLKL translocation without altering upstream RIP kinase levels.
Infarct Reduction and Contractile Recovery in Ex Vivo Models
Pharmacological evaluation in isolated heart models reveals significant cardioprotection following acute ischemic challenge. Administration of Necrostatin 2 racemate at reperfusion onset reduced myocardial infarct volume by nearly fifty percent relative to vehicle controls. Post-ischemic left ventricular contractility improved rapidly. Developed pressure recovery was sustained throughout the 120-minute reperfusion period. This functional salvage matched the protection conferred by classical ischemic preconditioning protocols; no further functional gain occurred when both interventions were combined. The absence of additive protection demonstrates a shared reliance on necroptotic inhibition. RIP1 kinase activity thus represents a critical single-point control node for cardiac cell survival.
Inhibition of Downstream MLKL Oligomerization and Translocation
Mechanistic mapping confirms that target engagement suppresses terminal execution events without altering apoptotic machinery. Membrane fraction isolation demonstrated that Necrostatin 2 racemate prevents MLKL oligomerization. Cytosolic retention of MLKL prevented membrane destabilization and cell rupture. Phosphorylation of RIP3 at Ser229 dropped significantly in treated tissue, whereas endogenous preconditioning bypassed RIP3 phosphorylation while still inhibiting MLKL translocation. Lipid peroxidation levels remained unaffected across all experimental groups; cleaved caspase-3 levels showed no significant shifts. These isolated biochemical endpoints confirm that necroptotic membrane pore assembly drives early reperfusion injury in cardiac tissue.
Convergence of Preconditioning Cascades on Necroptotic Execution
Endogenous preconditioning signals and direct small-molecule RIP1 inhibitors terminate at the same cellular threshold. Although ischemic preconditioning does not modify RIP1 or RIP3 expression levels, it effectively blocks downstream MLKL membrane integration. This convergent signaling reveals that MLKL translocation represents the final common gateway for necrotic cell death during myocardial ischemia-reperfusion injury. Pharmacological inhibition at the upstream RIP1 node provides an equivalent biological shield, validating target engagement in cardiac tissue under acute ischemic stress.