BBI-355 BBI355 from Selleck CHK1 Inhibitor in ecDNA-Driven Solid Tumors
Copy code to add this image to your page
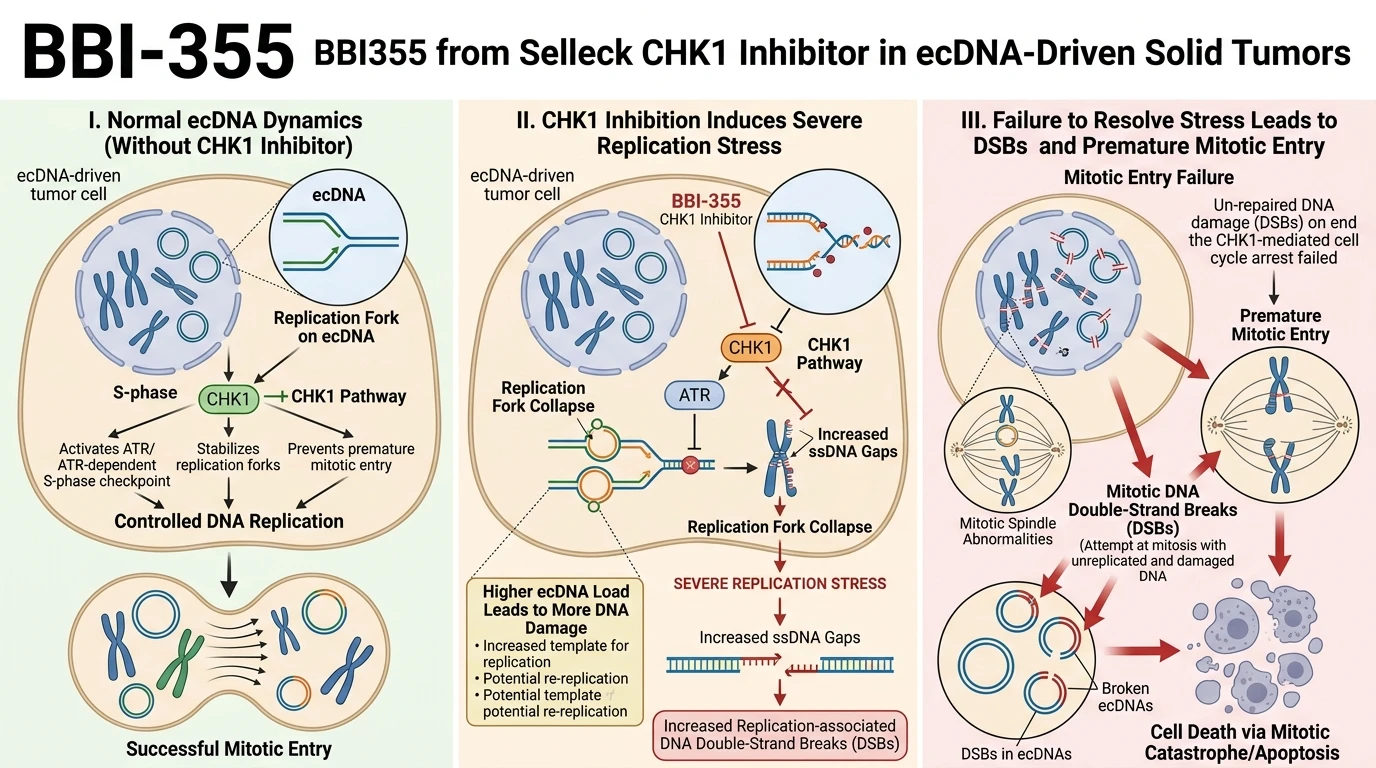
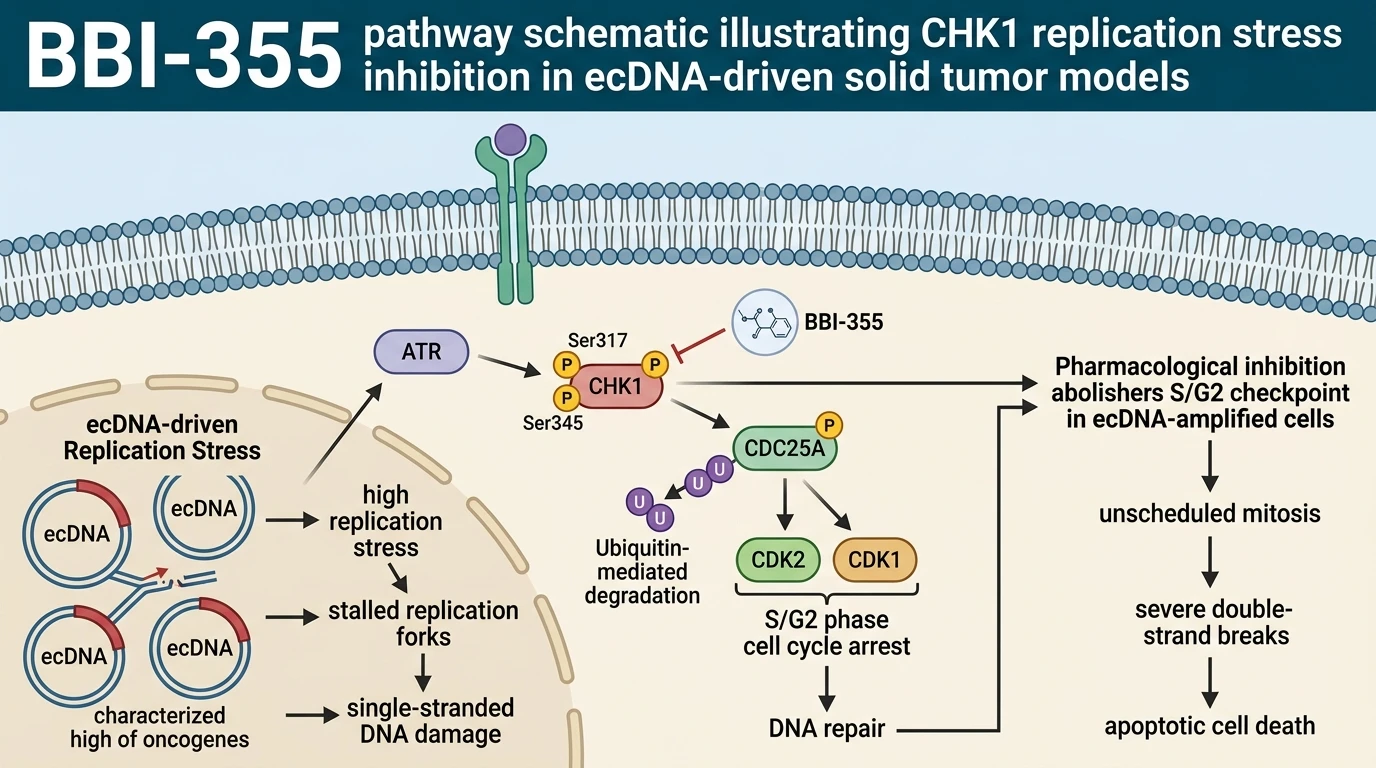
Replication stress represents a defining vulnerability in oncogene-amplified malignancies, particularly those driven by extrachromosomal DNA (ecDNA). Extrachromosomal DNA particles lack centromeres, allowing random non-Mendelian segregation during cell division and leading to focal copy number expansions of oncogenes such as EGFR, MYC, and CCNE1. This focal transcriptional hyperactivation overwhelms intracellular replication machinery, generating sustained stalled replication forks and single-stranded DNA gaps. To prevent immediate double-strand break accumulation and catastrophic premature mitosis, ecDNA-driven tumors rely heavily on the Ataxia Telangiectasia and Rad3-related (ATR) to Checkpoint Kinase 1 (CHK1) signaling cascade. CHK1 acts as a primary executioner kinase within this maintenance pathway, phosphorylating downstream targets such as CDC25A, WEE1, and RAD51 to coordinate S/G2 phase cell cycle arrest, replication fork stabilization, and homologous recombination repair.
Within this distinct pathophysiological framework, BBI-355 has been engineered as an oral, ATP-competitive Checkpoint Kinase 1 inhibitor designed as an extrachromosomal DNA-directed therapy (ecDTx). Experimental characterization in enzyme kinetic assays and binding affinity databases demonstrates high biochemical selectivity for CHK1 over related basophilic serine/threonine kinases, including CHK2 and CDK family members. Pharmacological evaluation of BBI355 from Selleck in cellular systems confirms robust target engagement, characterized by dose-dependent loss of CHK1 autophosphorylation at Ser296 and subsequent accumulation of unphosphorylated CDC25A.
The therapeutic rationale for BBI-355 exploits the synthetic lethality inherent to ecDNA-containing cancer cells. When CHK1 catalytic activity is blocked, ecDNA-amplified cells fail to enforce S and G2/M checkpoints in response to severe replication stress. Uncontrolled cyclin-dependent kinase 1 (CDK1) and cyclin-dependent kinase 2 (CDK2) activity forces cells with incompletely replicated ecDNA molecules into early mitosis. This aberrant cell cycle transition results in catastrophic replication fork collapse, extensive double-strand breaks marked by phosphorylated histone H2AX (γ-H2AX) accumulation, and rapid apoptotic cell death. Conversely, untransformed diploid cells with normal gene copy numbers maintain cell cycle integrity due to lower basal levels of replication stress.
Translational development of BBI-355 is actively ongoing in a Phase I/II clinical trial (NCT05827614) evaluating safety, pharmacokinetics, and initial antitumor efficacy in patients with refractory advanced or metastatic solid tumors harboring documented ecDNA amplifications, including pancreatic ductal adenocarcinoma and EGFR-amplified non-small cell lung cancer. The trial evaluates BBI-355 both as a single agent and in combination regimens. Combination strategies pair BBI-355 with the ribonucleotide reductase (RNR) inhibitor BBI-825 to deplete intracellular deoxyribonucleotide triphosphate (dNTP) pools and heighten replication stress. Other combination arms pair BBI-355 with targeted kinase inhibitors, including erlotinib for EGFR-amplified tumors and futibatinib for FGFR-driven lesions, to concurrently suppress oncogenic driver signaling and replication stress response mechanisms.
Therapeutic Evaluation and Pharmacological Characterization
Copy code to add this image to your page
BBI-355 acts as a selective oral inhibitor of Checkpoint Kinase 1 (CHK1), functioning as an extrachromosomal DNA-directed therapy. Tumors featuring high ecDNA copy numbers display elevated transcriptional activity and localized replication stress. By suppressing CHK1-mediated phosphorylation of CDC25A, BBI-355 overrides S and G2/M checkpoints. This action stalls replication fork progression, accelerates double-strand DNA break accumulation, and selectively induces synthetic lethality in ecDNA-amplified cancer cells while sparing diploid somatic tissues under physiological conditions.
Disruption of Replication Stress Adaptation in ecDNA Models
Extrachromosomal DNA elements generate excessive replication fork friction. Pharmacological engagement of CHK1 by BBI-355 disrupts this adaptive buffer system across patient-derived models. At nanomolar cellular concentrations, target occupancy exceeds 90% within two hours of administration. Rapid suppression of CHK1 catalytic activity prevents the inhibitory phosphorylation of CDC25A; consequently, CDC25A accumulates rapidly and inappropriately activates nuclear CDK1/2 complexes. This premature kinase activation forces cells with uncompleted DNA synthesis into early mitosis. Mitotic catastrophe occurs rapidly. Quantitative immunofluorescence demonstrates a dramatic surge in nuclear γ-H2AX foci—a hallmark of collapsed replication forks and double-strand DNA cleavage. In patient-derived pancreatic ductal adenocarcinoma organoids, treatment with BBI355 from Selleck led to severe chromatin fragmentation and irreversible commitment to apoptosis, while untransformed epithelial controls preserved nuclear structure and cell cycle progression.
Synergistic Lethality with Ribonucleotide Reductase and Kinase Inhibitors
Monotherapy efficacy often faces metabolic compensation. To counteract nucleotide recovery mechanisms, combination strategies leverage concurrent pathway inhibition. Co-administration of BBI-355 with the ribonucleotide reductase inhibitor BBI-825 severely depletes intracellular dNTP pools, accelerating replication fork arrest in S-phase cells. In EGFR-amplified non-small cell lung carcinoma xenografts, this dual blockade induced sustained tumor regression without significant hematological toxicity. Tumor volume decreased by 74% over 21 days. Furthermore, combining CHK1 blockade with receptor-specific tyrosine kinase inhibitors—such as erlotinib in EGFR-mutant settings or futibatinib in FGFR-driven models—simultaneously abrogates downstream driver survival signals and prevents ecDNA-mediated repair. Pharmacodynamic markers confirmed suppressed ERK phosphorylation alongside total clearance of phosphorylated CHK1.
Clinical Pharmacokinetics and Phase I Patient Stratification
Dosing regimens require careful optimization. In the ongoing Phase I/II trial (NCT05827614), oral administration of BBI-355 demonstrated predictable linear pharmacokinetics across tested dose tiers. Peak plasma concentrations were achieved within 2.5 hours post-dose. Systemic exposures maintained effective target coverage beyond the required pharmacodynamic threshold without inducing dose-limiting cytopenias. Biomarker-guided patient selection relies on fluorescence in situ hybridization (FISH) and next-generation sequencing (NGS) to identify focal ecDNA oncogene amplifications prior to enrollment. In heavily pretreated patients with metastatic solid tumors, early evaluation revealed clear evidence of target engagement and tumor stasis, establishing a rational baseline for expanding cohort evaluations in ecDNA-positive solid tumors.