Azenosertib (Zn-C3) Azenosertib inhibitor selective Wee1 suppression forces mitotic catastrophe
Copy code to add this image to your page
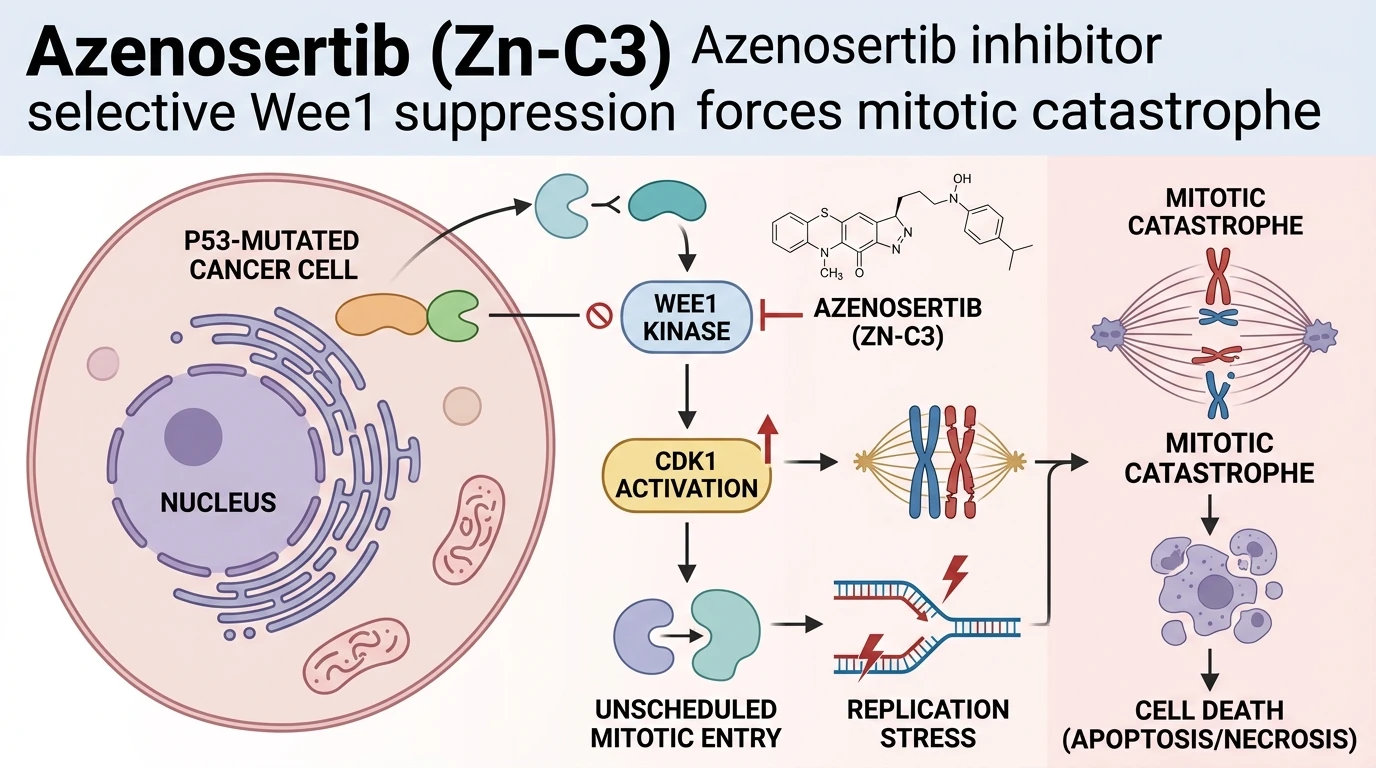
In cellular oncology, loss-of-function mutations in the TP53 gene represent the most common genomic alteration across human malignancies. The p53 protein serves as a primary regulator of the G1/S cell cycle checkpoint, halting cycle progression in response to double-strand DNA breaks to allow transcriptional activation of DNA repair machinery. When TP53 is mutated or deleted, tumor cells lose G1/S arrest capabilities. Consequently, these transformed populations become dependent on the G2/M checkpoint to repair DNA damage prior to genome segregation.
The G2/M transition is regulated by the serine/threonine kinase Wee1. Wee1 enforces G2 arrest by phosphorylating cyclin-dependent kinase 1 (CDK1) at the inhibitory Tyrosine-15 (Tyr15) residue. This phosphorylation keeps the CDK1-Cyclin B1 complex inactive, preventing cells with damaged DNA from initiating mitosis. In p53-deficient cancer cells, inhibition of Wee1 selectively destabilizes cell cycle arrest. Small-molecule suppression of Wee1 forces these cells to bypass G2 arrest and enter mitosis prematurely with unresolved structural DNA damage, culminating in mitotic catastrophe and apoptotic death.
Azenosertib (Zn-C3) is a highly potent, orally bioavailable inhibitor of Wee1 kinase designed to exploit this specific synthetic lethal vulnerability. Biochemical screening demonstrates that Azenosertib binds selectively to the ATP-binding pocket of Wee1. This binding blocks autophosphorylation and suppresses downstream Tyr15 phosphorylation of CDK1 in patient-derived tumor models. By abolishing Wee1-mediated CDK1 inhibition, the Azenosertib inhibitor causes rapid catalytic activation of CDK1-Cyclin B1. Tumor cells advance into M-phase despite widespread double-strand breaks or unresolved replication forks.
Premature mitotic entry induces severe structural damage to the genome. Cells entering mitosis with damaged template DNA experience aberrant spindle assembly, premature chromosome condensation, and severe spindle assembly checkpoint fatigue. These events lead to massive chromosome missegregation, micronuclei formation, and physical fragmentation of nuclear envelopes. In preclinical models, this biochemical cascade results in cell death characterized by mitotic catastrophe, distinct from classical caspase-dependent apoptosis observed with conventional antimetabolites.
Experimental evidence indicates that Wee1 inhibition disrupts replication fork stability during S-phase. Beyond its role at the G2/M boundary, Wee1 regulates CDK1 activity during DNA replication. Excessive CDK1 activation caused by Azenosertib triggers unscheduled origin firing, depletion of the single-stranded DNA binding protein RPA, and replication fork collapse. This dual action—inducing replication stress in S-phase while simultaneously abolishing the G2/M arrest—compounds genomic injury in rapidly proliferating tumor populations. Combining Wee1 inhibitors with statins also presents a compelling therapeutic axis. Statins perturb mevalonate metabolism, causing cell cycle dysregulation that increases dependency on Wee1 activity. In preclinical models of p53-mutated neoplasms, co-treatment with Azenosertib and statins produced enhanced cytotoxicity compared to monotherapy.
In addition to single-agent synthetic lethality, Azenosertib (Zn-C3) enhances the activity of DNA-damaging chemotherapeutic agents and targeted therapeutics. Exogenous DNA damage induced by platinum compounds or antimetabolites upregulates Wee1 activity as a compensatory survival mechanism. Administering an Azenosertib inhibitor alongside DNA-damaging chemotherapy blocks this survival response. Preclinical studies combining Wee1 suppression with agents like gemcitabine, carboplatin, or statins show synergistic reduction in tumor burden, particularly in high-grade serous ovarian cancer models exhibiting TP53 alterations.
Clinical translation of Azenosertib has advanced through early-phase trials evaluating safety, pharmacokinetics, and therapeutic activity. Phase 1/2 clinical trials in patients with advanced solid tumors and gynecological cancers demonstrate targeted pharmacodynamic engagement at tolerable doses. Monotherapy cohorts show objective responses in platinum-resistant ovarian carcinoma and uterine leiomyosarcoma. Observed toxicities—primarily hematologic effects like neutropenia alongside mild gastrointestinal symptoms—were manageable through intermittent dosing schedules. These clinical findings validate Wee1 inhibition via Azenosertib as a viable strategy for targeting p53-mutated solid tumors.
Therapeutic Evaluation and Pharmacological Characterization
Copy code to add this image to your page
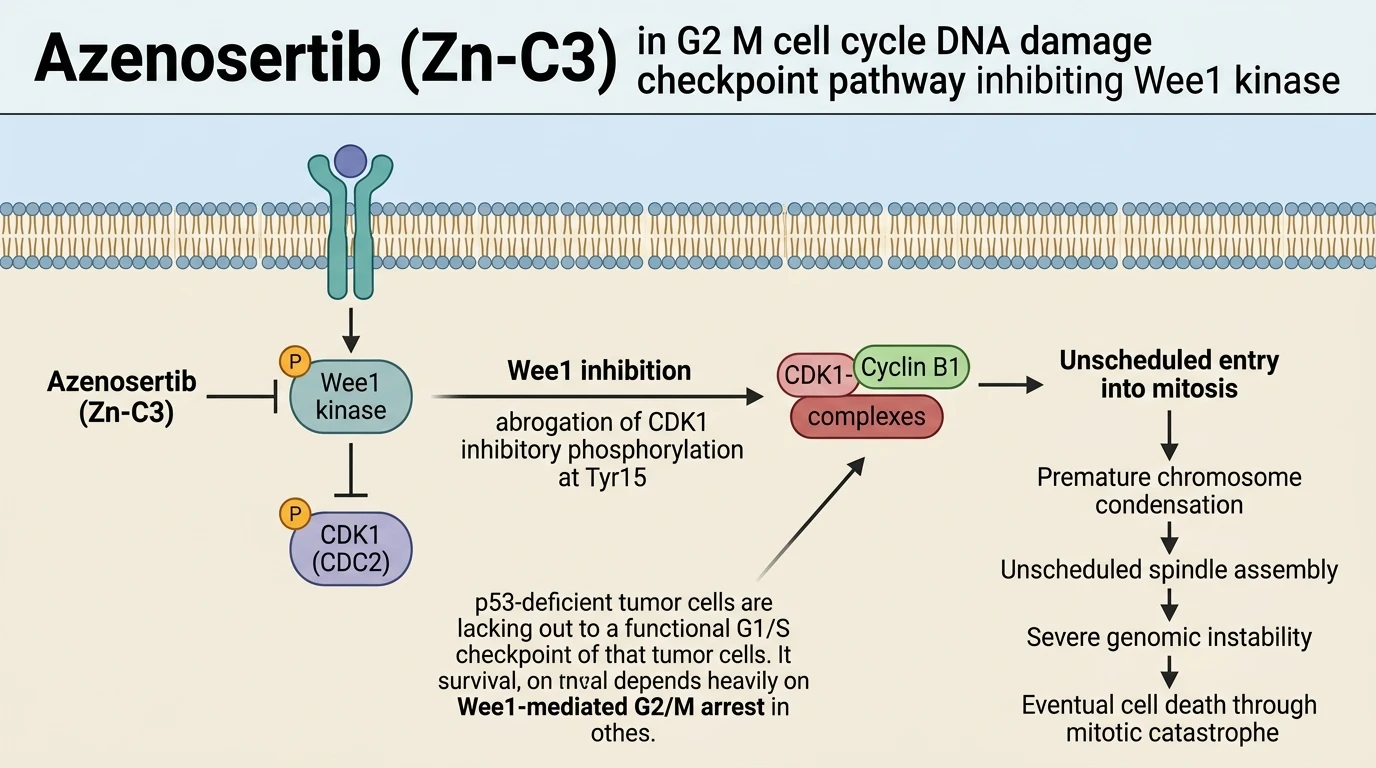
Azenosertib (Zn-C3) is a potent, oral Wee1 kinase inhibitor that overrides the G2/M cell cycle checkpoint. In p53-deficient cancer cells lacking a functional G1/S transition, Wee1 inhibition prevents inhibitory tyrosine-15 phosphorylation of CDK1. Uncontrolled CDK1 activation forces cells into premature mitosis prior to completing DNA repair, resulting in replication stress, chromosome missegregation, and mitotic catastrophe. Early clinical evaluation confirms anti-tumor efficacy and tolerable safety as both monotherapy and in combination regimens across advanced solid and gynecological malignancies.
Abrogation of Tyr15 Phosphorylation Triggers Premature Mitotic Entry
Wee1 kinase acts as a gatekeeper of mitotic entry. It phosphorylates CDK1 at Tyr15, maintaining the inactive state of the CDK1-Cyclin B complex. Treatment with the Azenosertib inhibitor abolishes this inhibitory signal. CDK1 activation follows immediately. In p53-deficient ovarian carcinoma lines, this kinase suppression forces unscheduled progression into mitosis. Cells bypass essential DNA repair windows. Unresolved replication forks collapse during chromosome condensation. This structural damage causes severe spindle defects and chromosome fragmentation. Experimental models confirm that cell death occurs via mitotic catastrophe rather than classic apoptotic pathways.
Phase 1/2 Trials Demonstrate Efficacy in Advanced Solid Tumors
Clinical evaluations of Azenosertib (Zn-C3) focus heavily on advanced solid malignancies with documented TP53 loss. In Phase 1/2 clinical trials, single-agent administration achieved objective responses in platinum-resistant ovarian cancer patients. Disease control rates remained consistent across multiple dosing cohorts. The observed safety profile proved manageable. Primary adverse events included transient neutropenia, fatigue, and low-grade nausea. These toxicities were mitigated using modified intermittent schedules. Combination arms pairing the Azenosertib inhibitor with carboplatin or gemcitabine demonstrated enhanced overall response rates in recurrent gynecological tumors.